
Uveitis
Understanding Uveitis in Children and Youth
Uveitis is an inflammatory eye condition that can occur alongside juvenile idiopathic arthritis (JIA) and other childhood rheumatic diseases. Because symptoms are not always visible, regular eye screening and early treatment are essential to protecting long-term eye health.
This page provides practical information, educational resources, videos, and lived experiences to help families better understand and navigate uveitis.
What is Uveitis?
Uveitis is inflammation inside the eye that can affect vision and eye health over time. It may occur in children living with juvenile idiopathic arthritis (JIA), particularly oligoarticular JIA, but it can also occur alongside other childhood rheumatic diseases.
Uveitis is not always connected to how active arthritis symptoms appear. Some children may have active eye inflammation even when joint symptoms are mild or well controlled.
Because symptoms are often difficult to notice early on, routine eye screening is an important part of ongoing care.
Common Symptoms

- Eye redness
- Eye pain
- Blurred vision
- Light sensitivity
- Floaters or dark spots in vision
- Decreased vision
Some children experience no obvious symptoms at all, which is why regular eye exams remain critically important.
Eye Screening Matters
Uveitis can sometimes develop silently, even when children feel well or arthritis symptoms appear controlled. Early detection and treatment help reduce the risk of long-term complications and vision loss.
Your pediatric rheumatology and ophthalmology teams will recommend regular screening schedules based on your child’s diagnosis and risk factors.
Videos Uveitis

Cory on living with Uveitis
Learn what it’s been like to manage his eye inflammation over the last 8 years from elementary to high school.

Uveitis virtual education session
Learn where inflammation occurs, what the risks of the inflammation and treatments are, and get a glimpse into uveitis research.
Do you have questions about Uveitis?
Uveitis
Regular eye screening is an important part of treatment.
Uveitis is an inflammatory eye condition that can occur alongside juvenile idiopathic arthritis (JIA) and other childhood rheumatic diseases. Because symptoms are not always visible, regular eye screening is an important part of early detection, treatment, and ongoing care.
Learning about uveitis can help families recognize symptoms, understand treatment options, and support long-term eye health.
Stories
Meeting someone who understands your experience can make a powerful difference. The Youth Mentorship Program exists to help young people build confidence, connection, and community.

Cassie’s Story
CASSIE Juvenile arthritis became a part of our family and our lives in September of 2006. One morning Cassie, then only 20 months old, wouldn’t walk when we took her out of her crib. […]

Caden’s Story – JIA, Uveitis & Needlephobia
Caden was diagnosed with JIA when she was just 3 years old. When we first noticed her limping, we thought she may have hurt her knee skiing. […]

Becki Zerr: No Stranger to JA and Uveitis
Uveitis (inflammation of the eye) is a serious complication occurring in 20% of children with Juvenile Arthritis, a condition that is hard to diagnose without regular eye screening. […]
FAQs
How often do patients go into remission? I have had inflammation in my eye for 7 years now and I can’t seem to get rid of it.
Uveitis can affect every child differently. Some children achieve long-term remission, while others may continue to experience ongoing inflammation that requires monitoring and treatment over time.
Although older studies suggested that some children could experience long-term vision complications, outcomes are improving significantly thanks to earlier diagnosis, better screening, closer follow-up, and more effective treatments.
Researchers are also working toward more personalized treatment approaches based on each child’s unique genetics, lifestyle, and environment, helping improve long-term care and outcomes.
What should we focus on while researching underlying causes for uveitis to help with the treatment (as parents)?
Researchers continue to study the many factors that may contribute to uveitis and childhood rheumatic diseases, including genetics, environment, lifestyle, and immune system function. While there is still much to learn, research has led to major improvements in diagnosis, monitoring, and treatment.
Parents and caregivers play an important role in this process. Asking questions, sharing observations, and discussing how treatments are working can help healthcare teams better understand each child’s unique experience.
As research and technology continue to advance, doctors are moving toward more personalized treatment approaches based on each child’s individual needs, genetics, and overall health.
My daughter has been diagnosed with panuveitis. Could you describe the main differences between uveitis and panuveitis?
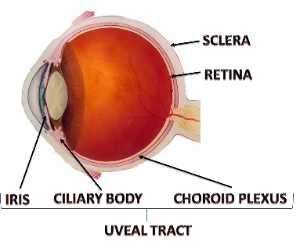
Uveitis refers to inflammation inside the eye, usually affecting part of the eye’s middle layer, known as the uveal tract. In children with juvenile idiopathic arthritis (JIA), the inflammation most commonly affects the front part of the eye, called anterior uveitis.
Panuveitis is a less common form of uveitis where inflammation affects the entire uveal tract — from the front of the eye to the back.
While both conditions involve eye inflammation, panuveitis may require closer monitoring and more extensive treatment. It can occur alongside childhood rheumatic diseases, infections, eye injuries, or other inflammatory conditions. Researchers continue to study why some children develop anterior uveitis while others develop panuveitis.
Can JIA and uveitis switch back and forth from joint pain to uveitis?
Children with JIA can develop uveitis at any time, even when their arthritis is not active. For some children with JIA, the arthritis inflammation becomes quiet, but they have continued uveitis requiring treatments. Similarly, arthritis can flare up at unpredictable times as well. The inflammation isn’t ‘switching back and forth’- the inflammation of JIA can involve different areas at different times.This is the reason that it is important for children with arthritis to have eye examinations as recommended by the pediatric rheumatologist and ophthalmologist even when a child appears to be well! In patients with both uveitis and arthritis we always try to select treatments that are effective for both areas of inflammation.
My doctor mentioned a 20% chance of uveitis among all JIA patients. If the patient has common characteristics such as young female and ANA positive, what does the probability of uveitis occurrence increase to for this subgroup?
Our Canadian research, looking at over 1,000 children newly diagnosed with JIA, has shown that the most important contributors to probability of uveitis are a positive ANA and being diagnosed at a young age. Uveitis was most commonly seen in children with either oligoarthritis or polyarticular rheumatoid factor negative JIA. We also saw that there was an incidence of new uveitis among these children of 2.8% per year for the 5 years of the study. This means that children with JIA need to continue to be screened for uveitis for at least 5 years after diagnosis.
With the current treatment that you are using, what are the expected outcomes?
Treatment outcomes for uveitis can vary from child to child, but advances in early diagnosis, monitoring, and treatment have significantly improved long-term outcomes for many families.
Newer biologic medications have transformed care by targeting specific parts of the immune system involved in inflammation. These treatments can help control inflammation more effectively and reduce the risk of long-term vision complications.
Researchers are also working toward more personalized treatment approaches based on each child’s unique genetics, lifestyle, and environmental factors. As research continues to evolve, doctors hope to better predict which treatments will work best, when treatment should begin, and when it may be safely reduced or stopped.
Is arthritis or uveitis common to show up in siblings?
Most forms of juvenile idiopathic arthritis (JIA) and uveitis are not common among siblings, although it can happen in some families. Certain types of JIA, such as Enthesitis-Related Arthritis (ERA), may be slightly more likely to occur in siblings than other subtypes.
Researchers believe that genetics, environmental factors, or a combination of both may contribute to why these conditions develop. However, more research is still needed to better understand these connections.
Although it is uncommon for siblings to develop JIA or uveitis, ongoing international research is helping doctors learn more about possible genetic and environmental influences.
Can an injury to the eye cause a flare-up?
Yes, uveitis can result from injury to the eye such as a blunt force to the eye or a foreign body in the eye. This usually results in iritis, which is inflammation of the colored part of the eye that surrounds the pupil. The iris is also one part of the eye that is typically inflamed in uveitis associated with JIA. There is also information from laboratory experiments suggesting that trauma in a joint can result in changes in certain molecules in the cornea of the eye (a part of the eye which is not primarily involved in uveitis associated with JIA).
What are the effects of having long term uveitis? Are flares the only time to worry about? Do eyes degrade similar to joints?
Long-term effects of uveitis can often be reduced through early diagnosis, regular monitoring, and appropriate treatment. Even when symptoms are mild or not visible, ongoing inflammation can still affect eye health over time, which is why routine eye exams are so important.
Potential complications of long-term uveitis may include:
- Reduced or blurry vision
- Cataracts (clouding of the eye’s lens)
- Increased eye pressure (glaucoma)
- Calcium deposits on the cornea (band keratopathy)
- Changes in how the pupil responds to light (synechiae)
Flares are important to monitor, but eye inflammation can sometimes continue quietly between flares without obvious symptoms. Regular follow-up with ophthalmology and rheumatology teams helps detect and manage changes early to protect long-term vision.
Is there any link between a mother’s use of antibiotics during pregnancy affecting the child’s microbiome?
There is some evidence that maternal use of antibiotics either before or during pregnancy or at the time of labor might result in changes in the microbiome of the child born to that mother. There have been no studies done specifically to investigate if maternal antibiotic use during pregnancy might affect the risk of the child developing JIA or uveitis. We are currently doing a research study to investigate how inflammation during pregnancy might influence future disease in the offspring. One facet of this study is to look at antibiotic use during pregnancy and the risk of the offspring having certain diseases later in life. We are also just about to begin a research project to study if the microbiome in the mouth influences the occurrence and course of JIA and if there is any connection with the oral microbiome and uveitis.
What medical exam can diagnose abnormal intestinal microbiome?
Assessing the intestinal microbiome is a specialized laboratory process and cannot be diagnosed through a regular physical exam alone. Researchers typically study the microbiome by analyzing stool samples to better understand the types of bacteria and other microorganisms living in the gut.
Scientists are also exploring whether the oral microbiome — including bacteria around the teeth and gums — may play a role in childhood rheumatic diseases. Research in this area is still evolving, but studies continue to improve our understanding of how the microbiome may influence inflammation and immune system activity.
Do children with uveitis ever grow out of it?
Every child’s experience with uveitis is different. Some children achieve long-term remission with treatment, while others may continue to experience ongoing inflammation that requires monitoring and care over time.
Although children do not typically “outgrow” uveitis in the traditional sense, early diagnosis, careful monitoring, and newer treatments can greatly improve long-term outcomes and may help stop the inflammatory process from continuing.
Researchers are also working toward more personalized treatment approaches based on each child’s unique genetics, lifestyle, and environmental factors, with the goal of improving treatment effectiveness and long-term remission.
What should we focus on while researching underlying causes for uveitis to help with the treatment (as parents)?
Research is crucial to advancing knowledge about the causes, mechanisms, and treatment for uveitis. In all our research now, including our studies relating to uveitis and childhood arthritis, we ensure that parents and patients are represented on our research teams. We feel it is important for patients and parents to contribute their ideas and perspectives as we develop research projects, interpret results, and disseminate our research results to end-users such as health care providers, administrators, and patients and families. For conditions such as uveitis and childhood arthritis, most of the time, we do not know the cause of the disease, we do not fully understand the mechanisms of the disease, we have treatments that are much improved but still not as predictably effective or as safe as we desire, and we have no insight into cure and prevention. However, there has been astonishing progress in gaining new knowledge. Based on that new knowledge, it is likely that uveitis and childhood arthritis occur because of multiple factors, including, as examples, genetics, environment, and lifestyle.
Parents can help by identifying possible factors that they wonder might influence the diseases’ occurrence and courses. We encourage parents to ask questions, share their thoughts, and participate fully in the process of learning more. Parents should not feel hesitant to ask questions and share their thoughts. It is also important for parents and patients to share their thoughts about the therapies they receive in terms of their effectiveness and side effects. As technologies advance, we can now aim to personalize treatment approaches; that is, rather than selecting therapies for groups of children with similar conditions, we are now beginning to individualize treatment choices for individual children based on their unique genetic, environmental, and lifestyle considerations. Parents and the patients themselves will be crucial in helping to make personalized choices for therapy.
My child has been uveitis free for two years now. She is on methotrexate injections. Is it safe to try methotrexate pills again?
Recently, a group of Canadian pediatric rheumatologists, pediatric ophthalmologists and patients and parents have been working together to develop standardized approaches for monitoring and treating children with uveitis associated with JIA . It was felt important to develop standardized approaches because there is some variability in how children with JIA uveitis are managed. In both the Canadian and similar United States guidelines that are being developed in children with JIA and uveitis who are starting treatment other than eye drops for uveitis, using injection of methotrexate is recommended over oral methotrexate.
In general, evidence suggests that injection of methotrexate works better for both arthritis and uveitis. Thus, if the child was on oral methotrexate before the injection and the switch was made to achieve better control of the JIA and/or uveitis, then switching back to oral methotrexate might or might not result in a flare. The decision the doctors might have to consider is not when to switch to back to oral methotrexate but when to try to discontinue methotrexate entirely. Deciding when to stop methotrexate would depend on how severe the uveitis was, how difficult it was to control, and if the child is on other medications. In the guidelines that are being developed, in children with uveitis that is well controlled on a medication such as methotrexate with or without other therapy, it is recommend that there be at least 2 years of well-controlled disease before tapering and then discontinuing the therapy.
So, in a child with at least 2 years of inactive disease one might soon consider beginning a slow taper of current medications rather than switching to oral methotrexate. But again, this depends a lot on the individual patient’s characteristics and treatments now and in the past. Studies are underway to gather evidence that will help guide when medications can be safely stopped without risking flare ups.
With the current treatment that you are using on your patients, what are the expected outcomes?
At the present time we can make decisions about treatments based on experiences from large groups of patients with similar conditions. However, the conclusions we make about the diseases and the treatments from studying the group as a whole do not always precisely apply to individual patients within the group; there is considerable variable in how individual patients will respond to treatment. Now, with new knowledge and technologies, we are beginning to aim for personalized approaches to therapy so that we can select therapies based on the individual’s genetic, lifestyle and environmental factors. We think this personalized approach will result in more uniform and effective responses to therapy. With earlier diagnosis, more rigorous follow up and monitoring of patients, and dramatically improved treatments, we anticipate the long-term outcomes of uveitis will greatly improve.
The new treatments that are available to treat uveitis (and arthritis) have transformed care and outcomes. The new treatments are referred to as biologic drugs because they are designed to target the precise molecules that participate in inflammation. Currently, these biologic drugs target molecules in the body that usually participate in inflammation. However, with more research we hope to be able to identify exactly what molecule or molecules participate in inflammation in the individual patient so that the exact correct choice of the biologic drug can be selected for that patient. Also, with more research we hope to be able to know better when the biologic drug should be started and when the medication can be safely stopped without causing the disease to recur. Of course, we are continuing to investigate what factors might be involved in causing uveitis to occur in the first place so that we can consider ways to prevent uveitis from occurring. New biologic treatments, that target an increasing number of proteins that contribute to inflammation, are being developed at a very rapid pace so new drugs are becoming available on a regular basis.
How long can a child receive Pred Forte before changing the treatment?
This is an excellent question and one which has been addressed by the committees in Canada and the United States which are developing standardized guidelines for treatment. The answer about the duration of Pred Forte treatment, which is steroid drop treatment, depends somewhat on the severity of the uveitis, the dose of the Pred Forte, and consideration of what other medications the child is taking. A very low dose of Pred Forte – that is, 1-2 drops per day, has been reported to be associated with negligible adverse effects. However, the risk of adverse effects such as cataracts increases with increasing dose. Children receiving more than 3 drops per day for an extended period of time are at greater risk for developing cataracts and children receiving less than 3 drops per day are reported to be 87% less likely than those receiving greater that 3 drops per day to develop cataracts. However, uncontrolled uveitis can also lead to cataracts. So, it is always a balance between good control of the uveitis and the risk of the medications. However, now that we have much better treatments for uveitis in JIA it is more common to be able to use only low doses of steroid drops in combinations with the other therapies.
How can we support uveitis treatment as parents at home? What actions can we undertake to support our child?
While the doctors can diagnose and monitor uveitis and prescribe medical treatments, it is essential for everyone on the care team, which includes parents and the patient, to recognize that, depending on the severity of the uveitis, other facets of the child’s life can be affected. If parents realize that there can be effects on the child’s psychological well-being, interpersonal relationships, recreational activities, and schoolwork effects, parents can help minimize these concerns. Doctors will try to educate the children about their disease, but parents can also play a role in helping the child understand their condition and the importance of the treatments. Generally, we advise parents to ensure their child enjoys as normal a life as possible, is physically active, eats a nutritious diet, and gets sufficient rest. Parents are encouraged to communicate with the child’s teachers to ensure they know that the child has uveitis and can tailor the child’s academic experience as required. Parents should also help other children in the family understand the affected child’s condition.
I have different experiences with different ophthalmologists. One will administer or ask me to administer Cyclogyl drops before the appointment while another does not use the drops to look into the eye looking for a flareup. I do get anxious about the two different processes. Can the eye be fully seen to find the flare without the Cyclogyl?
Recently, a group of Canadian pediatric rheumatologists, pediatric ophthalmologists and patients and parents have been working together to develop standardized approaches for monitoring and treating children with uveitis associated with JIA. It was felt important to develop standardized approaches because there is some variability in how children with JIA uveitis are managed. The specific question about when and if cyclogyl should be used was not part of our discussions but I can make some comments in response to this question.
First, I think it would be advisable to ask each of the ophthalmologists your question so you have a clear understanding about the rationale for their respective approaches. However, while I am not an ophthalmologist, I do have some thoughts about why there might be differences in approaches.
Cyclogyl is used to dilate the pupil of the eye – that is to make the pupil bigger and stay bigger for the duration of the exam. The pupil appears enlarged when it is dilated because the iris tissue moves outward (and the pupil appears small when it constricts because the iris moves inward to the centre of the eye). By dilating the eye the doctor will have a much wider window to look through into the eye making the eye examination easier. However, once the pupil is dilated an accurate test for vision cannot be done as the effects of the medication can cause blurring of this vision that may last for up to 24 hrs. Also, when the pupils are dilated with cylogyl it is not possible to accurately assess the movement of the iris; sometimes when the iris becomes inflamed, as it does in uveitis, parts of the iris can get stuck down to the lens behind or the cornea in the front; when this binding of the iris to adjacent tissues occurs, these areas of attachment might be less apparent than when the pupil is constricted (gets smaller). When the pupil is dilated with cyclogyl drops it won’t move to the constricted position so that it is more difficult to assess areas where the iris might be attached to the adjacent structures. So, one approach is for the ophthalmologist to have the vision exam and iris movement assessments done without using the dilating eye drops then add the eyedrops later to enlarge the pupil to make the visualization examination of eye with the slit lamp easier.
Do you have questions about Uveitis?
Additional Resources
Explore key topics to better understand treatment, manage symptoms, and support your child’s overall wellbeing.
Support Us
Get Confidence
Cassie + Friends is here to support you — every step of the way.
While Uveitis can feel complex at first, knowledge builds confidence. With the right information and support, families and young people can better navigate care and move forward with clarity.